Case Summary
A 27-year-old man with no significant medical history presented with a right submandibular mass. He was otherwise asymptomatic, without fevers, night sweats, unintentional weight loss, or additional symptoms. CT imaging demonstrated a 1.5 × 1.4 cm enlarged right level 2 cervical lymph node. Initial fine-needle aspiration (FNA) was negative, and the lymphadenopathy regressed spontaneously. 22 months later, the patient returned with recurrent cervical lymphadenopathy without constitutional symptoms. Repeat FNA and core biopsy were nondiagnostic, prompting excisional biopsy, which demonstrated nodular lymphocyte-predominant Hodgkin lymphoma (NLPHL). PET/CT demonstrated hypermetabolic right cervical level 2 and 4 lymph nodes without distant disease, consistent with stage 1A NLPHL according to the Ann Arbor staging system for lymphoma. Standard involved-site radiation therapy (ISRT) to 30 Gy was recommended; however, after shared decision-making prioritizing toxicity reduction, the patient elected treatment with very low-dose radiation therapy (VLDRT) using 4 Gy in 2 fractions.
Imaging Findings
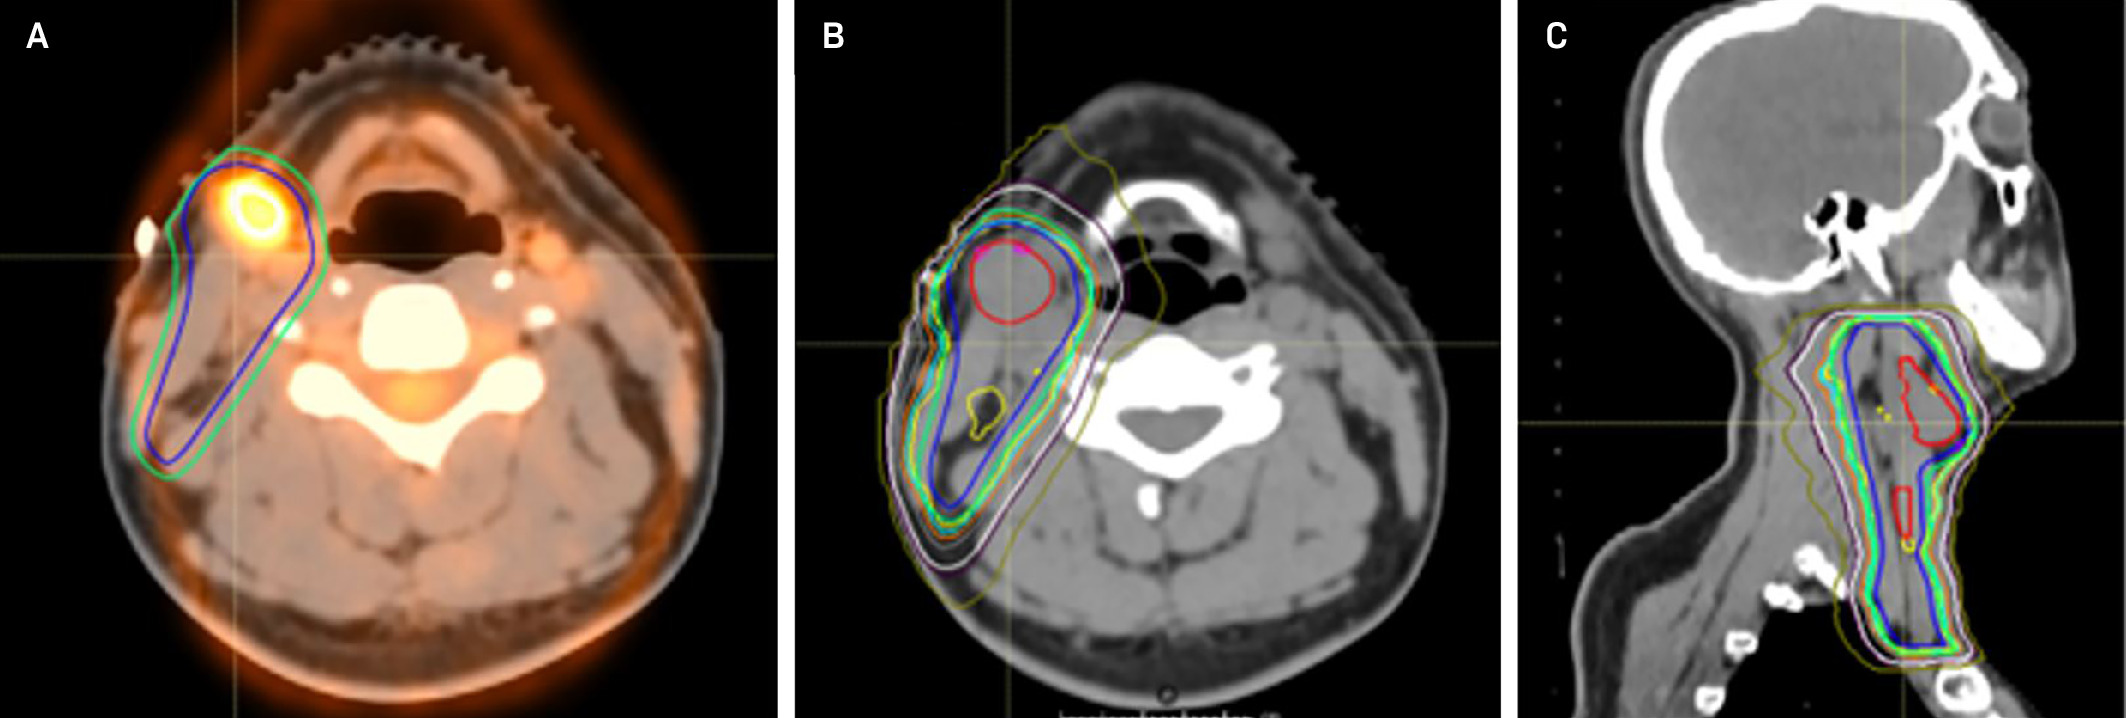
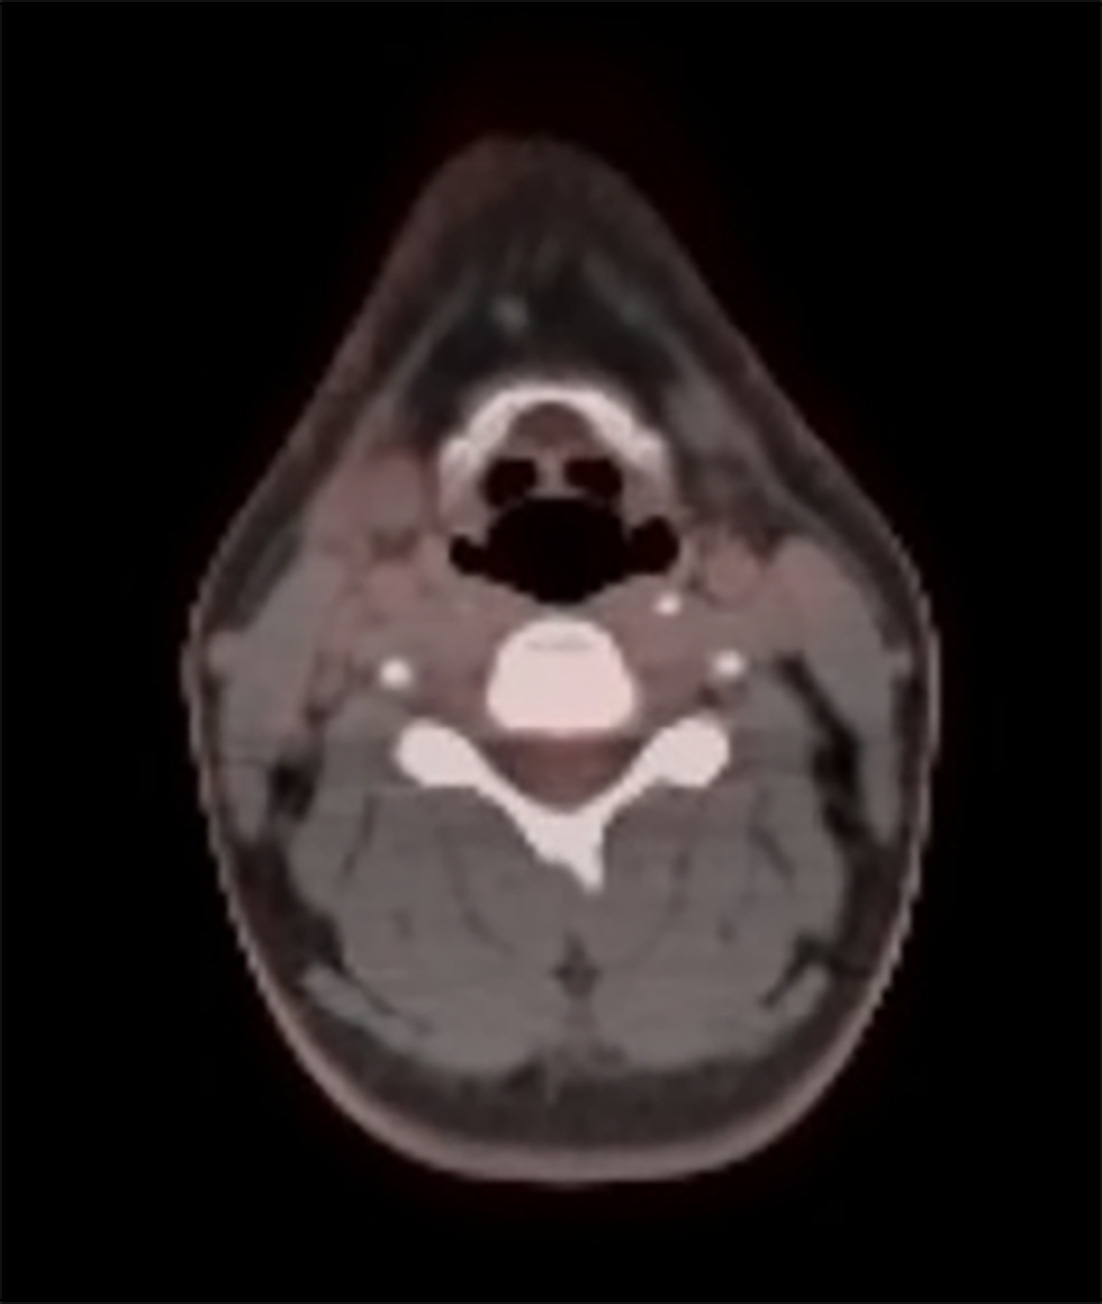
Initial contrast-enhanced CT imaging demonstrated an enlarged, right, level 2 cervical lymph node. Upon re-presentation, PET/CT demonstrated hypermetabolic right cervical level 2 and level 4 lymph nodes without distant disease, consistent with localized stage 1A NLPHL. Figure 1 demonstrates pretreatment PET/CT imaging showing metabolically active cervical lymphadenopathy and corresponding axial and sagittal ISRT treatment-planning images encompassing the involved nodal regions. No bulky or extranodal disease was identified. For treatment planning, an ISRT approach was taken. The grossly involved nodes (gross tumor volume) were expanded with a margin to account for subclinical disease, resulting in a clinical target volume (CTV) that encompassed the involved and adjacent/intervening nodal basins (i.e., in this case, the CTV consisted of the involved right cervical lymph node stations, levels 2 and 4, as well as the intervening lymph node station, level 3). A 3-mm margin upon the CTV was added to make the planning target volume, deemed adequate given mask immobilization and plan for daily image guidance. Intensity-modulated radiation therapy was delivered to 4 Gy in 2 fractions, with care given to minimize dose to thyroid, carotids, salivary glands, and oral cavity. Following completion of VLDRT (4 Gy in 2 fractions), repeat PET/CT obtained 3 months later demonstrated complete metabolic response with resolution of previously identified hypermetabolic cervical lymphadenopathy (Figure 2), consistent with remission.
Diagnosis
Stage 1A NLPHL involving right cervical level 2 and level 4 lymph nodes. Differential considerations included reactive lymphadenopathy, classical Hodgkin lymphoma (cHL), and indolent B-cell non-Hodgkin lymphoma (NHL) prior to excisional biopsy confirmation.
Discussion
NLPHL is a rare subtype of Hodgkin lymphoma accounting for approximately 5% of Hodgkin lymphoma cases and most commonly affecting young adult men.1 Unlike cHL, NLPHL is characterized by CD20-positive lymphocyte-predominant (“popcorn”) cells lacking CD15 and CD30 expression.2 Clinically, NLPHL behaves similarly to indolent B-cell NHL, with most patients presenting with localized peripheral lymphadenopathy and excellent long-term survival despite the risk of late relapse or transformation.3-5
Historically, early stage Hodgkin lymphoma was treated with extended-field radiation therapy, later replaced by involved-field radiation therapy and subsequently involved-site radiation therapy (ISRT) to reduce toxicity while maintaining disease control.6,7 Current guidelines recommend definitive ISRT to 30 Gy in 15 fractions for stage 1A NLPHL without clinical risk factors.8 When planning ISRT for stage 1 NLPHL, given that radiation is the primary treatment and no systemic therapy is given, the margins added to gross nodes should be accordingly generous to account for microscopic disease or subclinical spread,and as was done in this case, the involved and adjacent/intervening lymph node basins treated.7 Long-term progression-free survival with standard-dose radiation therapy approaches 85% to 92% at 8 to 10 years.1 Although effective, standard-dose radiation therapy exposes young patients to potential late toxicities, including cardiovascular disease and secondary malignancies.
Interest in treatment de-escalation has emerged given the radiosensitivity of indolent lymphomas. The Follicular Radiotherapy Trial, a randomized phase 3 study comparing 24 Gy with 4 Gy in indolent NHL, demonstrated meaningful responses even at very low doses.9 Additionally, a small 2009 series evaluating 4 Gy in 2 fractions for NLPHL demonstrated an overall response rate of 89% and complete response rate of 67%, although local relapse occurred in most patients during follow-up.10 These findings suggest VLDRT may provide excellent initial disease control, but the durability of long-term remission remains uncertain. Importantly, salvage therapy remained effective in relapsed patients.10
In the present case, a 27-year-old man with stage 1A NLPHL achieved complete metabolic response following VLDRT consisting of 4 Gy in 2 fractions. The patient prioritized minimizing treatment burden and long-term toxicity during shared decision-making. An adaptive approach was employed in which additional radiation therapy would be considered depending on the interval PET response. Treatment was well tolerated without acute toxicity, and follow-up PET/CT at 3 months demonstrated complete remission.
Radiation dose minimization carries important survivorship implications in young patients with Hodgkin lymphoma. Analyses from the Childhood Cancer Survivor Study demonstrated increased long-term risks of cardiovascular disease and secondary malignant neoplasms following radiation exposure.11,12 Survivors treated with supradiaphragmatic radiation doses of 30 Gy or greater experience significantly elevated mortality and cardiovascular risk persisting decades after therapy.12,13 Radiation-associated secondary malignancies, including breast, lung, and gastrointestinal cancers, also increase over time.12 Contemporary risk-adapted strategies using smaller treatment volumes and lower doses have reduced rates of severe chronic health conditions among survivors.14-17
This case suggests VLDRT may represent a reasonable treatment consideration in carefully selected patients with localized NLPHL prioritizing toxicity reduction. However, caution remains warranted given limited prospective evidence and the recognized risk of late relapse in NLPHL.5 Longer follow-up and prospective studies are needed to define the safety, efficacy, and durability of VLDRT strategies in this population.
Conclusion
Nodular lymphocyte-predominant Hodgkin lymphoma may demonstrate substantial radiosensitivity to very low-dose radiation therapy. This case demonstrates complete metabolic response following treatment with 4 Gy in 2 fractions in a young patient with stage 1A disease. Beyond reducing acute treatment burden, dose reduction may lessen long-term risks of cardiovascular disease and secondary malignancy in carefully selected patients. However, durability of remission following VLDRT remains uncertain, and larger prospective studies with prolonged follow-up are required before routine adoption of this strategy.